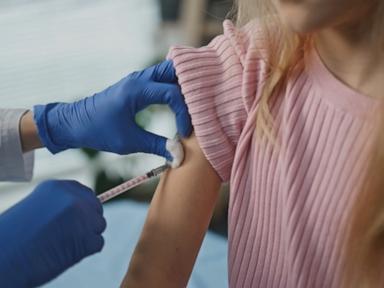
Every autumn, public health messaging pivots toward the same ritual. Clinics hang banners, pharmacies post signs, and healthcare providers urge the public to roll up their sleeves for seasonal immunizations. In recent years, the conversation has expanded past the traditional influenza vaccine to include updated boosters for SARS-CoV-2. Naturally, a logistical question dominates waiting rooms across the country: Should you take the flu and COVID shots together?
Yes, public health agencies and clinical guidelines confirm that receiving the influenza vaccine and the COVID-19 vaccine during the same visit is safe and medically acceptable. Co-administration eliminates the friction of scheduling multiple appointments, ensuring patients achieve dual protection ahead of peak viral transmission seasons without unnecessary delays. For a more detailed analysis into this area, we recommend: this related article.
Yet convenience tells only part of the story. Beneath the blanket recommendations lies a complex interplay of patient demographics, systemic immune response, logistics, and individual risk factors. To understand why co-administration became standard policy, we have to look past the press releases and examine the data, the physiological tradeoffs, and the operational realities facing modern healthcare delivery.
The Logistics of Co-Administration
Convenience remains the primary driver behind concurrent vaccination policies. Vaccine fatigue is real. Asking a population to visit a clinic twice within a span of weeks for two distinct jabs introduces significant friction into public health campaigns. Compliance drops precipitously with every extra hoop a patient must jump through. For further background on this development, detailed coverage can also be found on Psychology Today.
When the Advisory Committee on Immunization Practices and international health authorities evaluated safety data for simultaneous administration, the findings were clear. Co-administering both vaccines in opposite arms does not blunt the efficacy of either formulation. Immune systems are exposed to thousands of antigens daily; managing two distinct viral targets simultaneously is well within normal physiological capacity.
However, operational efficiency does not guarantee a uniform patient experience. Administering both injections at once alters the immediate post-vaccination profile.
Understanding the Immune Response and Side Effects
Any discussion about dual vaccination must address reactogenicity. When the immune system mounts a robust defense, it produces local and systemic inflammatory signals. These signals translate into familiar symptoms: sore arms, low-grade fevers, fatigue, and muscle aches.
When you combine two potent immune stimulators in one visit, the frequency of mild systemic side effects increases. Clinical observations indicate that patients receiving both shots simultaneously report higher rates of temporary fatigue, headache, and myalgia compared to those receiving either shot alone. These symptoms are transient, typically resolving within forty-eight hours, but they catch unprepared patients off guard.
A hypothetical example illustrates the clinical calculus. Consider an office worker with a critical product launch on Friday. If they receive a dual vaccination on Thursday afternoon, the cumulative systemic inflammatory response—manifesting as brain fog and fatigue—might impair their professional performance on Friday. Conversely, staggering the doses by a couple of weeks spreads out the immune activation, though it requires two separate trips and two rounds of mild arm soreness.
It is a classic risk-benefit tradeoff. Patients must weigh the temporary inconvenience of a stronger systemic reaction against the absolute protection afforded by immediate, simultaneous immunization.
High-Risk Populations and the Urgency of Timing
While healthy adults can deliberate over scheduling preferences, high-risk populations face a narrower margin of error. Older adults, immunocompromised individuals, and those with underlying chronic cardiorespiratory conditions cannot afford to delay protection.
For these groups, co-administration is not merely a matter of convenience; it is a critical safeguard. Every week spent unvaccinated during the ascent of a seasonal viral wave increases the probability of severe illness, hospitalization, or worse. The primary objective is establishing an antibody titer threshold before community transmission peaks.
Timing matters profoundly. Viral pathogens do not adhere to a predictable calendar. While historical trends point toward late autumn and winter surges, shifting weather patterns and novel viral variants can accelerate transmission cycles. Taking both shots in a single visit compresses the timeline to full protection, minimizing the window of vulnerability.
The Communication Challenge in Public Health
Public health messaging has historically struggled with nuance. Sweeping mandates and simplified talking points work well for mass compliance, but they often alienate populations that value individualized medical decision-making.
When authorities declare that co-administration is entirely safe and effective without acknowledging the temporary increase in side effects, trust erodes. Patients who experience moderate fever and severe fatigue after a dual shot may feel misled if they were told the process would be seamless. Transparent communication requires acknowledging that a stronger immune response can temporarily knock a patient flat.
Honest medical communication builds resilience. When individuals know what to expect—that a dual dose might require clearing the weekend schedule for rest—they are far more likely to complete their vaccination schedules year after year without harboring skepticism toward public health guidance.
Deciding how to proceed ultimately rests on individual health profiles, lifestyle constraints, and risk tolerance. For most, dropping the shield against both influenza and COVID-19 in one efficient visit remains the most pragmatic path forward. Yet recognizing the temporary cost in systemic side effects ensures that patients approach the clinic prepared, informed, and in control of their own healthcare choices.



