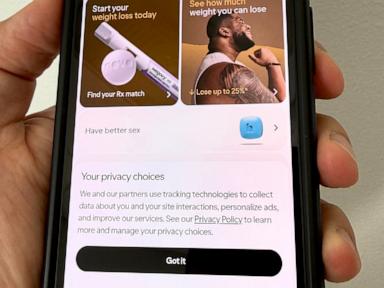
Digital health infrastructure operates under a fundamental misalignment between user acquisition models and medical privacy mandates. When direct-to-consumer platforms deploy analytics to optimize user conversion, they frequently introduce severe data exfiltration vectors. The structural failure of telehealth data governance is not driven by isolated coding anomalies or rogue actors; it is an inherent systemic outcome of merging high-efficiency digital marketing stacks with confidential health records.
The Three Vectors of Exfiltration
Understanding how health data leaks from telehealth portals requires mapping the technology stack into three discrete operational tiers: client-side event tracking, third-party software development kits, and backend application programming interface routing.
Client-side event tracking represents the most pervasive vulnerability. To measure user acquisition funnel efficiency, developers embed third-party marketing pixels and tracking scripts directly into front-end code bases. These scripts execute within the user's browser, capturing Document Object Model elements, form inputs, and navigation pathways. When a patient fills out an intake questionnaire specifying symptoms, mental health history, or pharmaceutical preferences, the browser often transmits those raw alphanumeric strings directly to advertising platforms alongside identifiers like Internet Protocol addresses and email hashes.
The underlying mechanism exploits the synchronous design of web browsers. The tracking script executes with the same privileges as the primary application logic, rendering structural separation between analytics collection and clinical data handling nearly impossible without explicit DOM sandboxing or server-side proxying.
The second tier involves third-party software development kits integrated into mobile applications. Unlike web browsers, native mobile operating systems lack native inspectable network boundaries for the average user, rendering embedded telemetry opaque. Many telehealth applications utilize analytics frameworks that automatically capture screen views, UI touch events, and local caching states. If a telemetry module captures an unmasked text view containing diagnostic codes or clinical notes, the SDK serializes that payload and transmits it to external telemetry endpoints. The engineering failure here stems from treating health software libraries with the same architectural laxity applied to e-commerce utilities.
The third vector resides in backend data routing and identity graph matching. Modern user acquisition strategies rely on server-to-server conversions APIs to bypass browser-based ad blockers. Telehealth platforms routinely hash and upload first-party customer lists to social media and search platforms for lookalike audience generation and attribution modeling. When customer relationship management databases containing clinical attributes or service categories are mapped directly against advertising network identity graphs, medical context is inadvertently merged with consumer profiles. This cross-contamination transforms anonymous health data into personally identifiable health records under regulatory scrutiny.
The Cost Function of Regulatory Non-Compliance
The economic model governing telehealth data governance has historically favored aggressive data sharing. Customer acquisition costs in virtual care markets are exceptionally high, often exceeding lifetime value projections during initial scale phases. Marketing optimization tools provide marginal improvements in conversion rates by feeding high-intent user behavioral signals back into ad-tech bidding algorithms.
[High Customer Acquisition Cost]
       │
       ▼
[Aggressive Optimization via Tracking Pixels]
       │
       ▼
[Data Exfiltration to Ad-Tech Platforms]
       │
       ▼
[Regulatory Enforcement & Litigation Cascades]
When platform operators weigh the marginal revenue gains of optimized ad-targeting against the historical probability of regulatory enforcement, the economic incentive calculation has frequently favored deployment. However, recent legal precedents and enforcement actions by the Federal Trade Commission and state attorneys general have fundamentally altered this cost function.
Civil penalties, mandatory consumer refunds, and the complete disgorgement of profits derived from illegally shared data introduce catastrophic tail risk. Furthermore, parallel civil litigation under state wiretapping statutes, the Electronic Communications Privacy Act, and comprehensive state privacy frameworks creates an unpredictable liability surface. A single improper tracking pixel implementation can expose an enterprise to class-action damages that dwarf its total venture funding or annual operating revenue.
Architectural Remediation Strategies
Eliminating data exposure vectors requires replacing legacy marketing architectures with privacy-preserving engineering patterns. Organizations must transition from reactive policy enforcement to deterministic data boundary enforcement.
First, engineering teams must implement server-side event proxying. Instead of allowing client browsers or mobile applications to communicate directly with third-party tracking endpoints, all telemetry must route through an internal, server-managed relay. This relay acts as a data diode. Before any payload leaves the corporate network, sanitization algorithms strip all Personally Identifiable Information, health condition indicators, and form field inputs. Only aggregated, non-sensitive conversion triggers are forwarded to downstream advertising networks.
Second, organizations must execute a complete telemetry inventory and dependency audit. Every script, pixel, and Software Development Kit must be cataloged, and its exact network payload must be intercepted and inspected using local proxy tools. Any third-party integration that lacks a fully executed Business Associate Agreement or strict data-processing addendum restricting secondary use for advertising must be purged immediately.
Third, access control models for clinical data pipelines must incorporate strict data minimization principles. Telemarketing and growth marketing teams must operate in an environment entirely decoupled from electronic health record databases. By utilizing synthetic data generation or deeply aggregated cohorts for growth analytics, platforms can preserve marketing optimization capabilities without exposing actual patient interactions to third-party data consumers.
Strategic Execution Framework
The remediation of telehealth data vulnerabilities requires structural transformation across engineering, legal, and executive leadership. The path forward demands an immediate operational pivot.
Establish a zero-trust telemetry policy across all web and mobile properties, blocking all unauthorized third-party script execution by default via strict Content Security Policies. Decouple marketing attribution infrastructure from clinical workflows by forcing all conversion tracking through isolated server-side proxy environments equipped with deterministic data scrubbing filters. Complete an exhaustive legal audit of historical data disclosures to identify potential liabilities under the FTC Health Breach Notification Rule and state privacy statutes before regulatory discovery commences. Align executive compensation and product key performance indicators with data minimization metrics rather than pure user acquisition velocity.